Keloid vs hypertrophic scar: fifteen years untreated
He walked away from the crash with flesh wounds on his jaw and thought he had been lucky. The hospital he went to was shut that day. Fifteen years later the scar had grown into a mass that hung down to his chest.
- Specialty
- Plastic and reconstructive surgery
- Patient
- Leon, 42, cocoa farmer
- Mechanism
- Motorbike crash, soft tissue wounds to the jaw
- Diagnosis
- Keloid
- Time untreated
- 15 years
- Procedure
- Surgical excision with skin graft
- Setting
- Volunteer surgical team, charity hospital ship
- day 0the crash
- same dayhospital closed
- monthsthe scar keeps growing
- 15 yearsa mass to his chest
- surgeryexcision and graft
The crash
Leon was riding pillion on a friend's motorbike when the friend lost control weaving through oncoming traffic. Both men were thrown from the bike. His friend was badly hurt. Leon got up with cuts around his jaw and considered himself the lucky one.
He went to the nearest hospital. It was closed.
He had eight children, very little money, and no realistic way to keep travelling in search of care for what looked like superficial wounds. So he made the decision almost anyone would have made in his position: he let them heal on their own.
What healing did instead
Skin repairs a breach by laying down collagen, and the process is supposed to stop when the gap is closed. In some people it does not. Fibroblasts keep producing collagen after the wound has sealed, and the scar keeps growing.
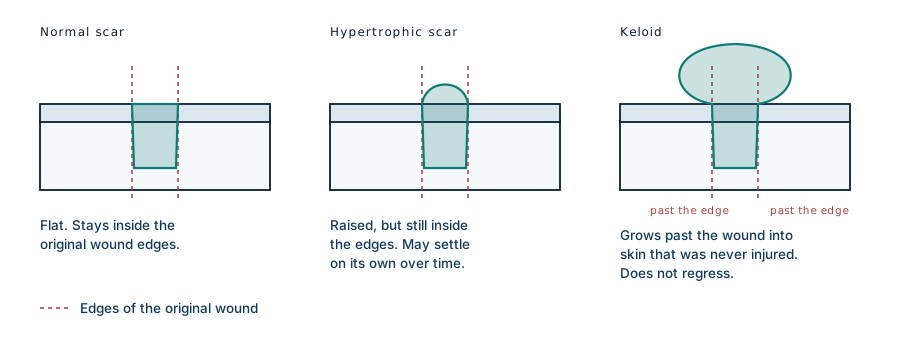
The distinction that matters clinically is where the growth stops. A hypertrophic scar is raised but stays within the boundaries of the original wound, and it often flattens over months or years without treatment. A keloid ignores those boundaries. It spreads sideways into skin that was never injured, it does not regress, and left alone it can keep enlarging for decades.
Keloids most often appear between the ages of 11 and 30, and they are substantially more common in people with darker skin. They are not cancer and they are not contagious. They can itch, hurt, bleed, and ulcerate at the surface, and when they grow across a joint or the neck they restrict movement.
Fifteen years
Leon's grew from the jawline downward until it hung below his chin. He described the problem in practical terms rather than cosmetic ones: there were tasks on the farm he could no longer do, and using a chainsaw had become impossible because the mass was in the way. He also spoke about the isolation, saying that few people had any sympathy left, and that he had stopped feeling he was living his life and was instead only getting through it.
That is the part of a keloid that the diagram cannot show. A benign scar that nobody would call a disease had taken his work, his social standing, and fifteen years.
Treatment
A volunteer plastic surgeon on a charity hospital ship excised the mass, and the defect left behind was covered with a skin graft. Leon said afterwards that he felt lighter, and that the weight lifted was not only the physical one.
The surgery is the visible part, but it is not the whole treatment, and this is where keloids differ from most masses. Cutting one out is itself a wound, in a person whose skin has already demonstrated that it overproduces scar. Excision on its own has a high rate of recurrence, and the new keloid can be larger than the original. That is why excision is normally combined with something else: steroid injections into the site, pressure, silicone dressings, or in selected cases radiotherapy, and why the follow-up matters as much as the operation.
That is an Amazon affiliate link. If you buy through it we may earn a small commission at no extra cost to you, and it makes no difference to what we write.
Silicone sheeting is the one self-applied treatment with reasonable evidence behind it, and it works best on scars that are still immature. It will not flatten an established keloid, and it is not a substitute for having a growing scar looked at.
What this case teaches
Nothing about this outcome was inevitable. The injury was minor, and the biology of keloid formation is well understood and treatable early, when the scar is small and steroid injection or pressure therapy will still control it. What produced fifteen years of disability was a closed door on the day it mattered, and no realistic way to try a second time. Access here is the entire difference between a scar and a disability, which makes it part of the medicine rather than background to it.
Written from the account published by Mercy Ships (Ainsworth G., “The Transformation After the Scars: Leon's Story,” 2018) and from standard references on keloid pathogenesis and management. Photographs of this patient are held by Mercy Ships and are not reproduced here. The diagram is original to MedicaseHub and may be reused freely. Affiliate disclosure: some links on this page are Amazon affiliate links. If you buy through them we may earn a commission at no extra cost to you, and it does not affect what we write. As an Amazon Associate we earn from qualifying purchases. This article is not medical advice; anyone with a growing or symptomatic scar should be assessed by a clinician, and early treatment gives far better results than late treatment. Read the full disclaimer.
One case, written up properly, when there is one worth sending
No schedule and no filler. When a case turns out to have something in it that is worth the time to explain, it goes out. Unsubscribe in one click.
Free · no spam · your address is never shared · built with KitRelated cases
- Parasitic twin: the twin with no heartA second head with eyes and lips, and no circulation of its own. Waiting would have made her weaker, not safer.
- Wooden foreign body on CT: the scan said gasWood reads as air on a scan. The clue that overturned the report was an infection that would not settle.
- Viper bite coagulopathy: the scan that showed nothingThree hours after the bite his blood could no longer clot. A normal ultrasound is what kept him out of theatre.